Every approved GLP-1 drug today is dosed weekly or daily. That is not an accident of chemistry — small peptides are cleared quickly, so weekly is the farthest the current generation of molecules can be stretched. Amgen's MariTide (maridebart cafraglutide) is engineered on a different platform entirely: a human monoclonal antibody fused to two GLP-1 analogue peptides, with GIP receptor antagonism built in. Half-life measured in weeks, not days. Phase 2 showed ~20% weight loss at 52 weeks on monthly dosing. Phase 3 began in 2025.
Key Takeaways
- First monthly GLP-1 therapy in late-stage development. MariTide is dosed every 4 weeks — sometimes less frequently depending on arm — not weekly.
- Antibody-peptide conjugate. Two GLP-1 agonist peptides tethered to a human IgG antibody that acts as a GIP receptor antagonist. The antibody scaffold is why the half-life is so long.
- Phase 2 (2024): ~20% body-weight loss at 52 weeks in obesity without diabetes, with no evidence of a plateau at the final data point.
- GIP antagonism — not agonism. This is the opposite of tirzepatide. The thesis: GIP antagonism may preserve fat-free mass and improve metabolic flexibility.
- Phase 3 MARITIME program launched 2025 across obesity and type 2 diabetes populations.
- Trade-off: fewer injections, but antibody manufacturing is more complex than small-peptide synthesis, with implications for cost and supply.
Why Monthly Matters
Adherence to injectable therapy drops with every missed shot. Real-world persistence on weekly GLP-1s at 12 months is well below 50%. If a therapy only requires 12 injections per year instead of 52, the mechanical barrier to staying on treatment falls dramatically. For patients who travel, work odd hours, or struggle with injection anxiety, monthly dosing isn't a convenience feature — it's an adherence intervention.
There's also a pharmacokinetic argument: smoother drug exposure. Weekly injections produce peaks and troughs within the dosing cycle. A monthly antibody with a longer half-life produces a flatter curve, which may translate into more consistent appetite suppression and fewer GI symptom swings.
The Molecule
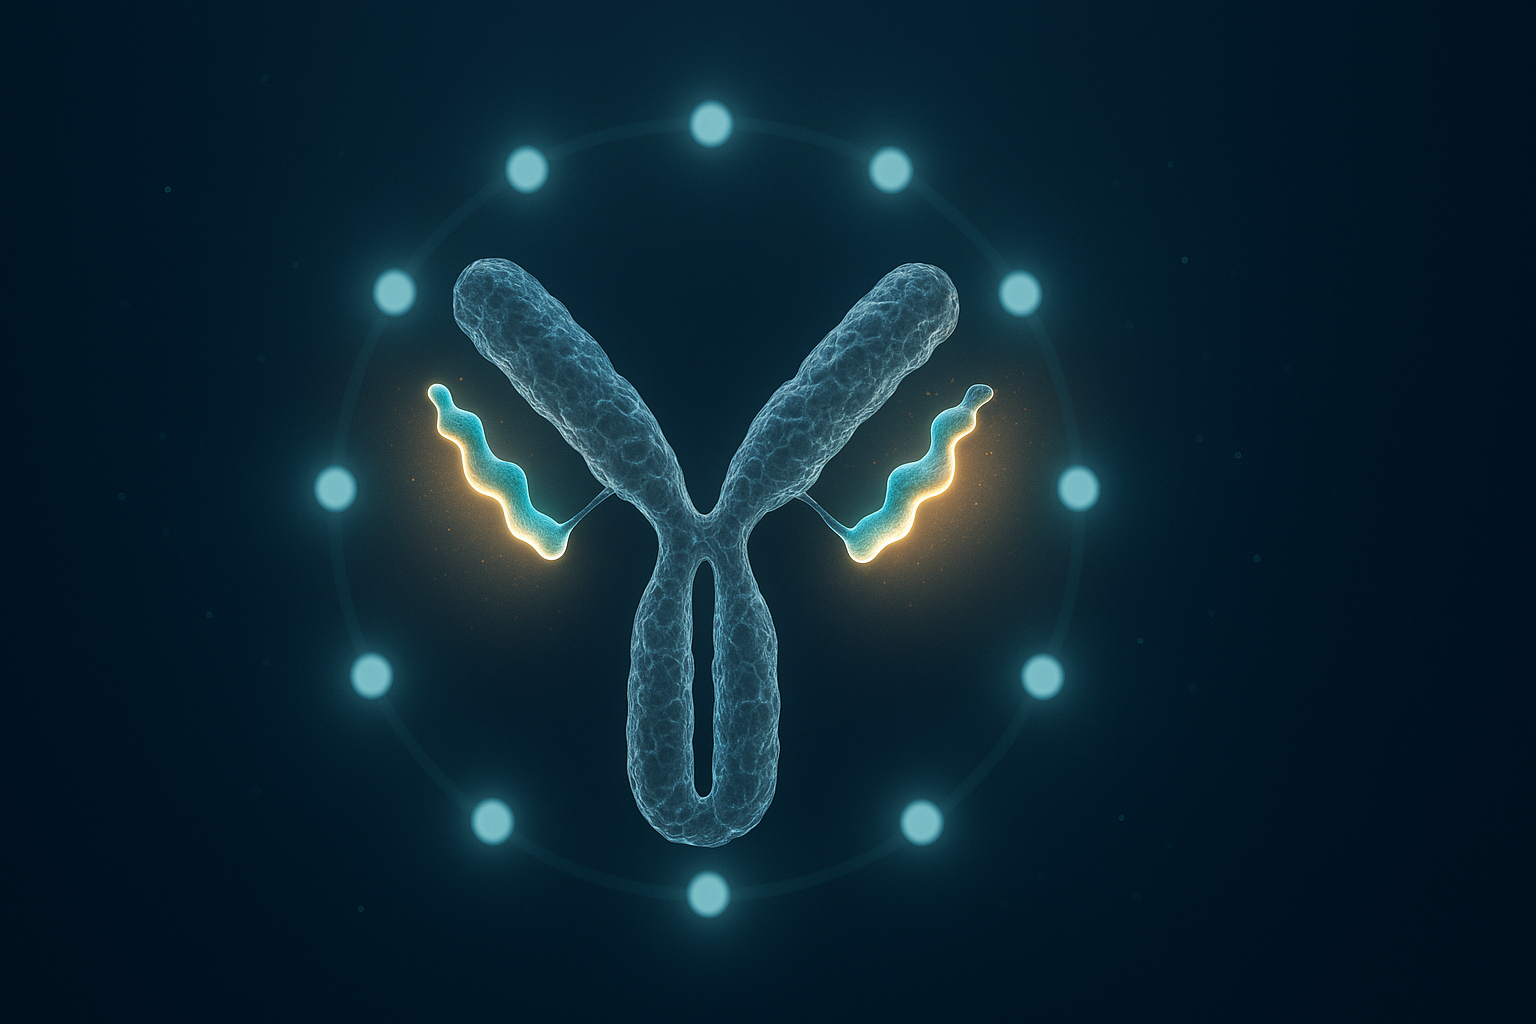
MariTide is unusual. It is not a peptide drug in the ordinary sense. The construct is:
- A human IgG antibody targeting the GIP receptor as an antagonist
- Two GLP-1 analogue peptides covalently tethered to the antibody
The GLP-1 peptides activate the GLP-1 receptor exactly like semaglutide or tirzepatide would. The antibody component is what makes it monthly — IgG antibodies have serum half-lives measured in weeks because of FcRn recycling. It also serves a second purpose: blocking the GIP receptor.
The GIP Antagonism Debate
Tirzepatide succeeds in part because it agonises both GLP-1 and GIP receptors. Amgen bet the opposite way: MariTide antagonises GIP while agonising GLP-1. The rationale draws on genetic and preclinical data suggesting that chronic GIP receptor loss-of-function is associated with lower adiposity, and that GIP antagonism may preserve fat-free mass preferentially during caloric restriction.
Whether the field will converge on agonism or antagonism is still open. The clean comparison does not exist yet. What Phase 2 showed is that GIP antagonism paired with GLP-1 agonism can produce ~20% weight loss — comparable in magnitude to the GIP-agonist tirzepatide at ~22%.
Phase 2 Data
Amgen reported Phase 2 results in late 2024. The 592-patient trial tested MariTide at multiple dose levels against placebo over 52 weeks:
- Highest dose arm: approximately 20% mean weight loss at 52 weeks
- Placebo: approximately 2.6%
- No apparent plateau at week 52 — weight was still trending down at study end
- Durability after discontinuation: post-treatment weight regain was slower than typically seen with weekly peptide GLP-1s, consistent with the long antibody half-life
In type 2 diabetes patients, weight loss and A1C reductions tracked expectations.
Safety Signals to Watch
GI adverse events dominated as expected for the class: nausea, vomiting, constipation. Rates and severity were in line with tirzepatide and semaglutide at matched escalation points. The analyst question that followed Phase 2 was whether a lower starting dose with slower titration can bring GI tolerability into the acceptable range without sacrificing efficacy — Phase 3 is designed to answer this.
A monthly antibody also raises long-tail safety questions: what happens when a patient wants to stop? With weekly semaglutide, the drug is substantially cleared within a few weeks. With MariTide, meaningful serum concentrations may persist for 8–12 weeks after the last dose. That is a durability feature for weight maintenance but a complication for anyone needing to discontinue quickly (e.g., unplanned pregnancy, serious adverse event, elective surgery).
Phase 3: MARITIME
Amgen launched the MARITIME Phase 3 program in 2025, covering:
- MARITIME-1 (obesity without diabetes)
- MARITIME-2 (obesity with type 2 diabetes)
- MARITIME-3 (obesity with cardiovascular disease)
Topline readouts are expected across 2026–2027. The clinical question is not merely "does MariTide work" — Phase 2 already answered that — but whether monthly dosing with GIP antagonism produces a differentiated efficacy, body-composition, or persistence profile versus weekly tirzepatide or semaglutide.
What This Means for the Pipeline
MariTide is the most clinically advanced example of a broader move toward less frequent GLP-1 dosing. Novo Nordisk is working on monthly amycretin. Several biotechs are exploring quarterly depot formulations. If MariTide delivers in Phase 3, the obesity-therapeutics industry is likely to split into two tiers:
- Weekly injectables and oral pills for new starts, titration, and patients who want short feedback cycles
- Monthly or longer-acting therapies for maintenance and long-term weight control, where adherence economics matter more than fine-grained dose adjustment
Frequently Asked Questions
What does "maridebart cafraglutide" mean?
It's the drug's generic name. "Maridebart" refers to the antibody component (anti-GIP receptor), "cafraglutide" refers to the GLP-1 peptide payloads. The suffix "-glutide" marks it as a GLP-1 class agent, matching the convention used by semaglutide and tirzepatide.
Is MariTide approved?
No. As of 2026 it is in Phase 3 development. No regulatory approvals exist. All data is from clinical trials.
Why antagonise GIP instead of agonising it like tirzepatide?
Chronic GIP receptor loss-of-function is associated with lower adiposity in human genetics. Amgen's hypothesis is that chronic GIP blockade mimics this phenotype pharmacologically. Tirzepatide bets the opposite way — short-term GIP agonism paired with GLP-1 agonism also produces strong weight loss. Both mechanisms have published support; the clean head-to-head doesn't exist yet.
Is monthly dosing better than weekly?
For adherence, likely yes. For dose titration flexibility and rapid discontinuation, no — monthly dosing is less forgiving. Trade-offs will become clearer in Phase 3.
How does MariTide compare to retatrutide?
Retatrutide is a triple agonist (GLP-1 + GIP + glucagon) delivered weekly, with the highest weight-loss ceiling observed in Phase 2 (~24%). MariTide is a GLP-1 agonist + GIP antagonist delivered monthly, with ~20% in Phase 2. Different mechanisms, different cadences, different market positions.
Could MariTide combine with other peptide therapies?
Theoretically yes — monthly GLP-1 maintenance plus a short-acting agent during escalation is one scenario researchers are discussing. No clinical trial of such combinations is underway.
Primary sources:
- Amgen Press Release — Phase 2 MariTide Data
- New England Journal of Medicine — MariTide Phase 2 publication
- ClinicalTrials.gov — MARITIME Phase 3 program
Research disclaimer: MariTide (maridebart cafraglutide) is an investigational drug and has not been approved by any regulatory agency. This article summarises publicly available Phase 2 data and ongoing Phase 3 program information for educational purposes. It does not constitute medical advice.